
EFSからピボタル試験への臨床開発 | 医療機器

早期フィージビリティ試験から医療機器のピボタルエビデンスへ

初期の良好なシグナルは、まだピボタル試験のエビデンス計画ではありません。ECLEVARは、EFSの結果、機器の変更、安全性シグナル、術者の習熟、そして残された不確実性を、次に行うべき試験の推奨と、米国、欧州、あるいはその両方で実行できる計画へと変えます。

  • Medical device specialists
  • Clinician-led interpretation
  • Integrated data and biostatistics
  • US and Europe evidence planning

EFSの実施主体は、ECLEVAR、他のCRO、大学施設、貴社自身のチームのいずれでも構いません。臨床、技術、運用、規制の資料一式を、現状のまま検討します。

早期フィージビリティ試験の後に

初期シグナルからピボタル試験への準備が整うまで

問うべきは結果が有望だったかどうかではありません。残された不確実性が、検証的試験の費用、規模、規制上のリスクを正当化できるほど小さいかどうかです。

図1 · ピボタル試験への準備状況と意思決定ゲート

Pivotal readiness assessed against a decision gate Seven readiness dimensions are drawn as horizontal ranges standing for the illustrative residual uncertainty attached to each pivotal assumption, each with a marker at an illustrative position. A gold decision gate crosses the plot and the area beyond it is shaded as the resolved side. Four dimensions, device maturity, population definition, data completeness and site scalability, sit entirely beyond the gate and are drawn in navy with solid markers. Three dimensions, procedure consistency, endpoint measurability and operator learning curve, still cross or fall short of the gate and are drawn in coral with hollow markers. Four possible next clinical steps are listed below. The first two, additional EFS learning and a traditional feasibility study, represent a need for further learning before any confirmatory commitment. The final two, a US pivotal study and an EU MDR clinical investigation, represent later evidence-generating pathways. The figure is an illustrative decision framework: it carries no units, no scores and no study results, and the positions shown were not calculated from any sponsor program. In this vertical layout each dimension is a label with its own measurement strip underneath, and the decision gate is drawn as repeated aligned gate segments, one per strip, rather than as one continuous vertical line. Commit to a pivotal studywhen the criticalassumptions are sufficientlyresolved. DECISION GATE Device maturity Procedure consistency Population definition Endpoint measurability Operator learning curve Data completeness Site scalability More uncertainty Less uncertainty Range: illustrative residualuncertainty. Marker: illustrativeposition. Illustrative decision frameworkonly. No units, scores or studyresults. POSSIBLE NEXT CLINICAL STEP Additional EFS learning Key assumptions remain unresolved Traditional feasibility study Near-final design; pivotal readinessstill developing US pivotal study Definitive safety and effectivenessevidence EU MDR clinical investigation Clinical safety, performance andbenefit
Pivotal readiness assessed against a decision gate Seven readiness dimensions are drawn as horizontal ranges standing for the illustrative residual uncertainty attached to each pivotal assumption, each with a marker at an illustrative position. A gold decision gate crosses the plot and the area beyond it is shaded as the resolved side. Four dimensions, device maturity, population definition, data completeness and site scalability, sit entirely beyond the gate and are drawn in navy with solid markers. Three dimensions, procedure consistency, endpoint measurability and operator learning curve, still cross or fall short of the gate and are drawn in coral with hollow markers. Four possible next clinical steps are listed below. The first two, additional EFS learning and a traditional feasibility study, represent a need for further learning before any confirmatory commitment. The final two, a US pivotal study and an EU MDR clinical investigation, represent later evidence-generating pathways. The figure is an illustrative decision framework: it carries no units, no scores and no study results, and the positions shown were not calculated from any sponsor program. In this vertical layout each dimension is a label with its own measurement strip underneath, and the decision gate is drawn as repeated aligned gate segments, one per strip, rather than as one continuous vertical line. Commit to a pivotal study when the criticalassumptions are sufficiently resolved. DECISION GATE Device maturity Procedure consistency Population definition Endpoint measurability Operator learning curve Data completeness Site scalability More uncertainty Less uncertainty Range: illustrative residual uncertainty. Marker:illustrative position. Illustrative decision framework only. No units, scoresor study results. POSSIBLE NEXT CLINICAL STEP Additional EFS learning Key assumptions remain unresolved Traditional feasibility study Near-final design; pivotal readiness still developing US pivotal study Definitive safety and effectiveness evidence EU MDR clinical investigation Clinical safety, performance and benefit
Pivotal readiness assessed against a decision gate Seven readiness dimensions are drawn as horizontal ranges standing for the illustrative residual uncertainty attached to each pivotal assumption, each with a marker at an illustrative position. A gold decision gate crosses the plot and the area beyond it is shaded as the resolved side. Four dimensions, device maturity, population definition, data completeness and site scalability, sit entirely beyond the gate and are drawn in navy with solid markers. Three dimensions, procedure consistency, endpoint measurability and operator learning curve, still cross or fall short of the gate and are drawn in coral with hollow markers. Four possible next clinical steps are listed below. The first two, additional EFS learning and a traditional feasibility study, represent a need for further learning before any confirmatory commitment. The final two, a US pivotal study and an EU MDR clinical investigation, represent later evidence-generating pathways. The figure is an illustrative decision framework: it carries no units, no scores and no study results, and the positions shown were not calculated from any sponsor program. The layout is a single labeled plot with the seven dimensions stacked in one column and the four possible next clinical steps arranged in two rows of two beneath it. Commit to a pivotal study when the criticalassumptions are sufficiently resolved. DECISION GATE Device maturity Procedure consistency Population definition Endpoint measurability Operator learning curve Data completeness Site scalability More residual uncertainty Less residual uncertainty Range: illustrative residual uncertainty. Marker: illustrative position. Illustrative decision framework only. No units, scores or study results. POSSIBLE NEXT CLINICAL STEP Additional EFS learning Key assumptions remain unresolved Traditional feasibility study Near-final design; pivotal readinessstill developing US pivotal study Definitive safety and effectivenessevidence EU MDR clinical investigation Clinical safety, performance andbenefit
Pivotal readiness assessed against a decision gate Seven readiness dimensions are drawn as horizontal ranges standing for the illustrative residual uncertainty attached to each pivotal assumption, each with a marker at an illustrative position. A gold decision gate crosses the plot and the area beyond it is shaded as the resolved side. Four dimensions, device maturity, population definition, data completeness and site scalability, sit entirely beyond the gate and are drawn in navy with solid markers. Three dimensions, procedure consistency, endpoint measurability and operator learning curve, still cross or fall short of the gate and are drawn in coral with hollow markers. Four possible next clinical steps are listed below. The first two, additional EFS learning and a traditional feasibility study, represent a need for further learning before any confirmatory commitment. The final two, a US pivotal study and an EU MDR clinical investigation, represent later evidence-generating pathways. The figure is an illustrative decision framework: it carries no units, no scores and no study results, and the positions shown were not calculated from any sponsor program. The layout is a single labeled plot with the seven dimensions stacked in one column. Commit to a pivotal study when the critical assumptions aresufficiently resolved. DECISION GATE Device maturity Procedure consistency Population definition Endpoint measurability Operator learning curve Data completeness Site scalability More residual uncertainty Less residual uncertainty Range: illustrative residual uncertainty. Marker: illustrative position. Illustrative decision framework only. No units, scores or study results. POSSIBLE NEXT CLINICAL STEP Additional EFS learning Key assumptions remainunresolved Traditional feasibilitystudy Near-final design; pivotalreadiness still developing US pivotal study Definitive safety andeffectiveness evidence EU MDR clinicalinvestigation Clinical safety, performanceand benefit
早期フィージビリティ試験が自動的にピボタル試験につながるわけではありません。意思決定ゲートは、プログラムをさらなる初期学習へ差し戻すこともあります。
01

EFSが明らかにしたこと

原理の実証、初期の臨床安全性情報、機器の機能性、そして患者選択に関する初期の知見。まだ確立できていないこととは切り分けて示します。

02

不確実なまま残ること

欠落した追跡、不安定な推定値、一貫しない評価項目の定義、そして小規模なデータセットでは支えられない前提。次の試験が解消すべきことなので、明示的に挙げます。

03

機器構成の安定性

構成が確定しているか、確定に近いか、どの被験者がどのバージョンに曝露したか、そして残る変更が検証的デザインに何をもたらすか。

04

評価項目と対象集団

想定する集団が施設をまたいで再現できる程度に厳密に定義されているか、そして評価項目が臨床的に意味を持ち、大規模に収集できるか。

05

術者の習熟

観察されたシグナルが機器そのものを反映しているのか、まだ機器の扱いへの習熟を反映しているのか。施設および術者の影響は、推定値を症例数設計に持ち込む前に検討します。

06

一つの評価として読む

Endpoints cannot be fixed before the population is defined, and the site model cannot be sized before the endpoints settle. If that earlier decision is still open, see our 早期フィージビリティ試験サービス.

意思決定ゲート

規模を広げる前に次の試験を選ぶ

通常、五つの道筋が選択肢になります。まだピボタル試験に進むべきでないという推奨も有用な結果です。時期尚早な検証的試験が費やしてしまう予算と規制上の立ち位置を守るからです。

米国ピボタル試験

該当する状況
機器と試験に関する前提が、検証的評価に耐えるだけ成熟している
未解決の問い
想定するFDA経路に向けた安全性と有効性のエビデンス
計画上の含意
FDAとの折衝、ピボタル試験の設計、IDEの準備、拡張可能な米国での運用

欧州における検証的臨床試験

該当する状況
欧州の適合性評価に向けたエビデンスが優先される
未解決の問い
EU MDRのエビデンス戦略のもとでの安全性と臨床性能
計画上の含意
EU MDR第62条および附属書XV、ISO 14155:2026、所管当局および倫理委員会の経路

米国と欧州の協調プログラム

該当する状況
二つの市場がいずれも戦略的で、意味のある整合が可能である
未解決の問い
どの要素を共有でき、どの要素が法域固有のまま残るか
計画上の含意
地域ごとの適合を文書化した、中核プロトコル戦略

追加のフィージビリティ試験またはブリッジング試験

該当する状況
設計は進んでいるが、ピボタル試験の前提がまだ成熟していない
未解決の問い
術者間の再現性と、大規模での運用上の実行可能性
計画上の含意
より安定した機器を対象に、より厳密な手法で行う大規模な探索的試験

さらなる組み入れの前に行う機器またはプロトコルの改良

該当する状況
機器または手技の変更がまだ保留になっている
未解決の問い
これまでの知見が、これから検討しようとしている構成にも当てはまるかどうか
計画上の含意
変更管理、プロトコルの改訂、該当する場合はIDEの補遺

The appropriate route is device-specific and should be confirmed with the relevant regulatory authorities and qualified regulatory specialists. This is a planning aid, not a regulatory algorithm. Once the US route is selected, see our FDA IDE臨床試験の支援.

入り口となる関与

EFSからピボタルへの戦略ワークショップ

貴社の臨床、規制、開発の責任者と行う構造化された作業セッションで、ECLEVARがEFSを実施したかどうかにかかわらず実施します。次の臨床試験に踏み切る前にスポンサーが必要とする、意思決定に足る成果物を生み出すよう設計されています。

ご提供いただくもの

  • プロトコルおよびその改訂
  • 機器のバージョン履歴
  • 安全性およびモニタリングの所見
  • 逸脱
  • 評価項目の充足状況
  • リスティングおよび利用可能な解析
  • 治験責任医師および術者からのフィードバック
  • 想定する主張と対象市場

お持ち帰りいただくもの

  • 所見と残存する不確実性のマップ
  • 次の試験として推奨する道筋
  • 機器の準備状況と変更管理の評価
  • 候補となる対象集団と評価項目の枠組み
  • 米国および欧州の規制上の論点整理
  • データと統計の優先順位を含む実行ロードマップ
ECLEVARの手法

ECLEVARが移行計画をどう組み立てるか

四つのフェーズです。次のフェーズが始まる前に各フェーズが一つの意思決定を完了させるため、最後になってからではなく、定められた地点で中止、方向転換、あるいは決断ができます。

01

EFSのエビデンスを診断する

主な作業
プロトコルとその改訂、機器のバージョン、モニタリング所見、逸脱、安全性データ、評価項目の充足状況、リスティング、治験責任医師のフィードバックの精査
得られる判断
EFSが確立したことと、確立しなかったこと
成果物
所見と残存する不確実性のマップ

02

意思決定ゲートと次の試験の道筋を定める

主な作業
想定する主張と対象市場に照らした、機器と手技の成熟度の評価
得られる判断
五つの道筋のうちどれをエビデンスが支持するか、そしてその理由
成果物
根拠を伴う次の試験の推奨

03

エビデンスアーキテクチャを構築する

主な作業
対象集団と評価項目の枠組み、エスティマンドと症例数の前提、そして市場ごとの規制上の論点整理
得られる判断
市場をまたいで共有されるものと、法域固有のまま残るもの
成果物
臨床、統計、規制の各面からのエビデンスアーキテクチャ

04

実行への引き継ぎを準備する

主な作業
管理された文書移管、施設と組み入れのフィージビリティ、ガバナンス、リスク登録簿、そして期間と予算の前提
得られる判断
決断するか、学習の段階をもう一つ挟むか、いったん止めるか
成果物
実行ロードマップと引き継ぎ資料
市場戦略

科学的な中核は一つ、米国と欧州の判断は別

単一の科学的中核が二つの市場を支えることはできます。その背後にある規制上の判断は別のままであり、一方のために生み出したエビデンスが他方で自動的に受け入れられるわけではありません。EFSの推定値が症例数設計を支えるには不安定すぎる場合は、その旨を述べ、どうすれば使えるようになるかを示します。

EFSのデータセットで確認すること

  • 欠測、評価項目の充足状況、そして追跡
  • ばらつき、信頼区間、暫定的な効果量
  • 施設、術者、学習曲線の影響
  • アウトカム定義の一貫性と判定委員会の要否
  • 機器バージョン間の差異とプロトコル逸脱

なぜ合同で行うのか

統計的な不安定さ、臨床的な妥当性、運用上の負担は、たいてい同じ問題を三つの角度から見たものです。別々に検討すると、紙の上では筋が通るのに実際には実行できない設計が生まれます。だからこそ、当該領域の医師、生物統計家、臨床オペレーション、データマネジメントが同じデータセットに一緒に向き合います。

想定する主張
米国ピボタル試験Safety and effectiveness for the intended FDA submission
欧州における検証的試験Safety and clinical performance under the EU MDR
協調プログラムOne claim set, two evidence objectives written down separately
対象集団と評価項目
米国ピボタル試験Sized for the confirmatory question and the US site network
欧州における検証的試験Sized for the conformity-assessment question and the country mix
協調プログラムHarmonized definitions where scientifically and regulatorily appropriate
機器構成
米国ピボタル試験Change control traced through the IDE framework where applicable
欧州における検証的試験Change control traced through the clinical investigation documentation
協調プログラムOne controlled version history, referenced by both submissions
統計的枠組み
米国ピボタル試験Estimand, comparator, and analysis sets aligned to the FDA question
欧州における検証的試験Analysis aligned to the clinical evidence strategy under the EU MDR
協調プログラムShared statistical principles, separately justified conclusions
規制当局との折衝と申請
米国ピボタル試験Q-Submission and IDE pathway as applicable
欧州における検証的試験Competent authority and ethics pathway, by country
協調プログラムSequenced or parallel interactions, with no automatic mutual acceptance

欧州では、承認と倫理審査はEU MDRおよび適用される各国の手続に基づいて行われ、所管当局と申請手続は関係する国によって異なります。欧州の検証的臨床試験は、米国のピボタル試験と自動的に規制上等価となるものではありません。

図2 · 米国および欧州連合のエビデンスアーキテクチャ

One scientific foundation, separate regulatory decisions One shared scientific foundation is shown as four stratified courses: intended use and population, endpoint definitions, statistical principles, and data standards with the benefit-risk rationale. Two structurally different regulatory structures are shown. The United States structure is a solid navy block covering FDA interaction, IDE and pivotal planning, and safety and effectiveness, capped by the FDA premarket decision. The European Union structure is an outlined block covering EU MDR clinical evidence, Article 62 and Annex XV, and clinical safety, performance and benefit, capped by the EU MDR conformity assessment. A dashed coral rule labeled separate regulatory decisions divides the two. Evidence generated for one market may inform the other, but it is assessed under each market's own requirements, and there is no automatic mutual acceptance. In this vertical layout the shared scientific foundation is presented first, at the top of the sequence, followed by the United States structure, then the separation, then the European Union structure. The foundation is read before the two structures rather than drawn beneath them. One scientific foundation,separate regulatorydecisions. SHARED SCIENTIFIC FOUNDATION Intended use andpopulation Endpoint definitions Statistical principles Data standards andbenefit-risk rationale UNITED STATES FDA interaction IDE and pivotal planning Safety and effectiveness FDA premarket decision Separate regulatory decisions EUROPEAN UNION EU MDR clinical evidence Article 62 and Annex XV Clinical safety, performanceand benefit EU MDR conformity assessment Evidence generated for one marketmay inform the other, but it isassessed under each market's ownrequirements. There is no automaticmutual acceptance.
One scientific foundation, separate regulatory decisions One shared scientific foundation is shown as four stratified courses: intended use and population, endpoint definitions, statistical principles, and data standards with the benefit-risk rationale. Two structurally different regulatory structures are shown. The United States structure is a solid navy block covering FDA interaction, IDE and pivotal planning, and safety and effectiveness, capped by the FDA premarket decision. The European Union structure is an outlined block covering EU MDR clinical evidence, Article 62 and Annex XV, and clinical safety, performance and benefit, capped by the EU MDR conformity assessment. A dashed coral rule labeled separate regulatory decisions divides the two. Evidence generated for one market may inform the other, but it is assessed under each market's own requirements, and there is no automatic mutual acceptance. In this vertical layout the shared scientific foundation is presented first, at the top of the sequence, followed by the United States structure, then the separation, then the European Union structure. The foundation is read before the two structures rather than drawn beneath them. One scientific foundation, separateregulatory decisions. SHARED SCIENTIFIC FOUNDATION Intended use and population Endpoint definitions Statistical principles Data standards and benefit-risk rationale UNITED STATES FDA interaction IDE and pivotal planning Safety and effectiveness FDA premarket decision Separate regulatory decisions EUROPEAN UNION EU MDR clinical evidence Article 62 and Annex XV Clinical safety, performance and benefit EU MDR conformity assessment Evidence generated for one market may inform the other,but it is assessed under each market's own requirements.There is no automatic mutual acceptance.
One scientific foundation, separate regulatory decisions One shared scientific foundation is shown as four stratified courses: intended use and population, endpoint definitions, statistical principles, and data standards with the benefit-risk rationale. Two structurally different regulatory structures are shown. The United States structure is a solid navy block covering FDA interaction, IDE and pivotal planning, and safety and effectiveness, capped by the FDA premarket decision. The European Union structure is an outlined block covering EU MDR clinical evidence, Article 62 and Annex XV, and clinical safety, performance and benefit, capped by the EU MDR conformity assessment. A dashed coral rule labeled separate regulatory decisions divides the two. Evidence generated for one market may inform the other, but it is assessed under each market's own requirements, and there is no automatic mutual acceptance. In this layout the two structures are placed side by side and visibly stand on the foundation, which spans the full width beneath them. One scientific foundation, separate regulatory decisions. Separate regulatory decisions FDA premarket decisionUNITED STATESFDA interactionIDE and pivotal planningSafety and effectiveness EU MDR conformity assessmentEUROPEAN UNIONEU MDR clinical evidenceArticle 62 and Annex XVClinical safety, performanceand benefit SHARED SCIENTIFIC FOUNDATION Intended use and population Endpoint definitions Statistical principles Data standards and benefit-risk rationale Evidence generated for one market may inform the other, but it is assessed undereach market's own requirements. There is no automatic mutual acceptance.
One scientific foundation, separate regulatory decisions One shared scientific foundation is shown as four stratified courses: intended use and population, endpoint definitions, statistical principles, and data standards with the benefit-risk rationale. Two structurally different regulatory structures are shown. The United States structure is a solid navy block covering FDA interaction, IDE and pivotal planning, and safety and effectiveness, capped by the FDA premarket decision. The European Union structure is an outlined block covering EU MDR clinical evidence, Article 62 and Annex XV, and clinical safety, performance and benefit, capped by the EU MDR conformity assessment. A dashed coral rule labeled separate regulatory decisions divides the two. Evidence generated for one market may inform the other, but it is assessed under each market's own requirements, and there is no automatic mutual acceptance. In this layout the two structures are placed side by side and visibly stand on the foundation, which spans the full width beneath them. One scientific foundation, separate regulatory decisions. Separate regulatory decisions FDA premarket decisionUNITED STATESFDA interactionIDE and pivotal planningSafety and effectiveness EU MDR conformity assessmentEUROPEAN UNIONEU MDR clinical evidenceArticle 62 and Annex XVClinical safety, performance and benefit SHARED SCIENTIFIC FOUNDATION Intended use and population Endpoint definitions Statistical principles Data standards and benefit-risk rationale Evidence generated for one market may inform the other, but it is assessed under each market's own requirements. There is noautomatic mutual acceptance.
構造を示す図にすぎません。いかなる当局またはノーティファイドボディによる承認、認証、推奨を表すものではありません。
受払管理

ECLEVARの経営陣

移行に割り当てられるチームは、機器、治療領域、対象市場、契約範囲によって変わります。判断を担うのは以下の人々です。

Dr Mark Da Costa

最高執行責任者兼循環器領域責任者、シニアコンサルタント心臓外科医

Markは、心臓外科のコンサルタントとしての25年の経験と、ノーティファイドボディでの臨床審査における上級管理職としての実地経験を併せ持ちます。想定する主張、評価項目、患者集団、術者の習熟、機器の成熟度に照らして、ピボタル試験への準備状況を検証します。

意思決定の段階: device and procedure maturity, cardiovascular and structural heart evidence strategy.

Dr Nikhil Khadabadi

最高医学責任者、整形外科および脊椎、シニアコンサルタント外科医

NHSの整形外科医であり、クラスIII埋植機器の評価経験と、ロボット手術研究における治験責任医師の経験を有します。対象集団の定義と手技の標準化に、外科および埋植の視点をもたらします。

意思決定の段階: population, procedure reproducibility, and separating device performance from operator experience.

Sebastien Meier Piantanida

最高データ責任者

移行の全体にわたりデータ戦略とバイオメトリクスを担い、EDCおよびeCOAのガバナンス、ピボタル試験に向けたデータセットの整備を含みます。EFSのデータセットが、検証的デザインの拠り所となる前提を支えられるかどうかを見極めます。

意思決定の段階: data completeness, statistical assumptions, and endpoint collectability.

Dawn Heimer

戦略クリニカルアドバイザー、米国

Dawnは、医療機器スポンサーに対し、FDAとの臨床面の折衝、および早期フィージビリティで得た学びから次の臨床開発段階への移行について助言しています。その経験には、FDAのPre-SubmissionおよびQ-Submissionでの折衝を約15件計画・実施したこと、そして過去3年間に早期フィージビリティ試験を管理したことが含まれます。契約した助言範囲に含まれる場合にECLEVARのプログラムに参画します。

意思決定の段階: FDA engagement strategy, interpretation of FDA feedback, and EFS-to-pivotal transition planning.

参画者の氏名、担当範囲、規制上の窓口は契約範囲の中で確定します。米国の規制対応の主導は、指名されたFDA規制責任者、または別途起用する有資格のFDA専門家を通じて、スポンサーが引き続き担います。

ノーティファイドボディにおける過去の職位は、経歴上の背景としてのみ記載しています。ECLEVAR MedTechは独立しており、いかなるノーティファイドボディとも提携しておらず、その推奨も受けていません。

スポンサーからよくある質問

EFSからピボタル試験への移行:よくある質問

EFSからピボタル試験への移行とは何ですか。
It is the work between the end of an early feasibility study and the commitment to the next clinical study. It establishes what the EFS resolved, what remains uncertain, whether the device configuration and endpoints can support confirmatory evidence, and which route the evidence actually supports. The output is a documented recommendation and an executable plan, not a restatement of the EFS results.
ECLEVARは他のCROが実施したEFSを評価できますか。
Yes. This can be a valid starting point. We review the protocol and amendments, device version history, monitoring findings, deviations, safety data, endpoint completion, and available listings and analyses, together with investigator feedback. The output is a findings and residual uncertainty map your team can challenge before any recommendation on the next study is made.
米国で実施したEFSは、欧州の臨床試験の計画に役立ちますか。
It can inform the planning substantially, including device maturity, procedure standardization, endpoint behavior, and patient selection. It does not mean the data will be accepted for a European conformity assessment. European clinical evidence requirements are assessed under the EU MDR on their own terms, and the acceptability of any dataset is a separate question from its usefulness for design.
ピボタル試験よりも、もう一度フィージビリティ試験を行うほうが適切なのはどのような場合ですか。
When the device or procedure is still changing, when outcomes still track operator experience, when the intended population has not stabilized, or when the available estimates are too unstable to size a confirmatory study. In those cases a bridging or additional feasibility study usually costs less than a pivotal study that has to be amended, extended, or repeated.
一つの臨床プログラムで米国と欧州の双方のエビデンス戦略を支えられますか。
Sometimes a single scientific core can serve both, with regional modules for documentation, submissions, and site requirements. It is never automatic. The two regulatory decisions are made under different frameworks, and acceptance of information in one jurisdiction does not by itself establish sufficiency for the other. Alignment should be planned deliberately and confirmed with each authority.
ECLEVARは次の臨床試験を実施できますか。
Yes, where the scope fits our capabilities. European clinical investigation delivery is our core execution capability, covering feasibility, site selection, start-up, monitoring, data management, biostatistics, and medical writing. Execution scope is agreed separately from the transition work, and the transition engagement is not conditional on awarding us the study.

公式コンテンツ

Eclevarが署名するコンテンツ

当社のチームおよびパートナーであるBSI、TÜV SÜD、RegenLabが作成したホワイトペーパー、お客様の声、出版物。

BSIとEclevarがEU MDRについて執筆したホワイトペーパーの表紙

ホワイトペーパー · BSI x Eclevar

BSIとEclevarによるEU MDRに関するホワイトペーパー

ノーティファイドボディであるBSIと共同で執筆しました。EU MDR 2017/745のもとで臨床エビデンスが何を示さなければならないか、そしてデータが越えるべき品質の水準はどこにあるかを実務的に整理しています。それは、欧州のデータセットが審査官の前に置かれる前に満たす水準と同じものです。

ホワイトペーパーを読む

PMCF試験 · 再生医療 · EU5か国

複雑な試験を実施するEclevarの能力について、お客様の声

EclevarはRegenLabの慢性創傷製品に関するPMCFプログラムを実施しています。EU5か国14施設で160名を対象とする無作為化試験であり、糖尿病性足潰瘍と静脈性下腿潰瘍の双方を対象としています。この協働は、EclevarのISO 14155に関する専門性とMilo Studioプラットフォームを組み合わせ、試験デザインから最終報告書までを担うものです。

« Eclevar, with its tailored approach and the advanced Milo Studio platform, represents a significant strategic advantage. »Antoine Turzi、CEO、RegenLab
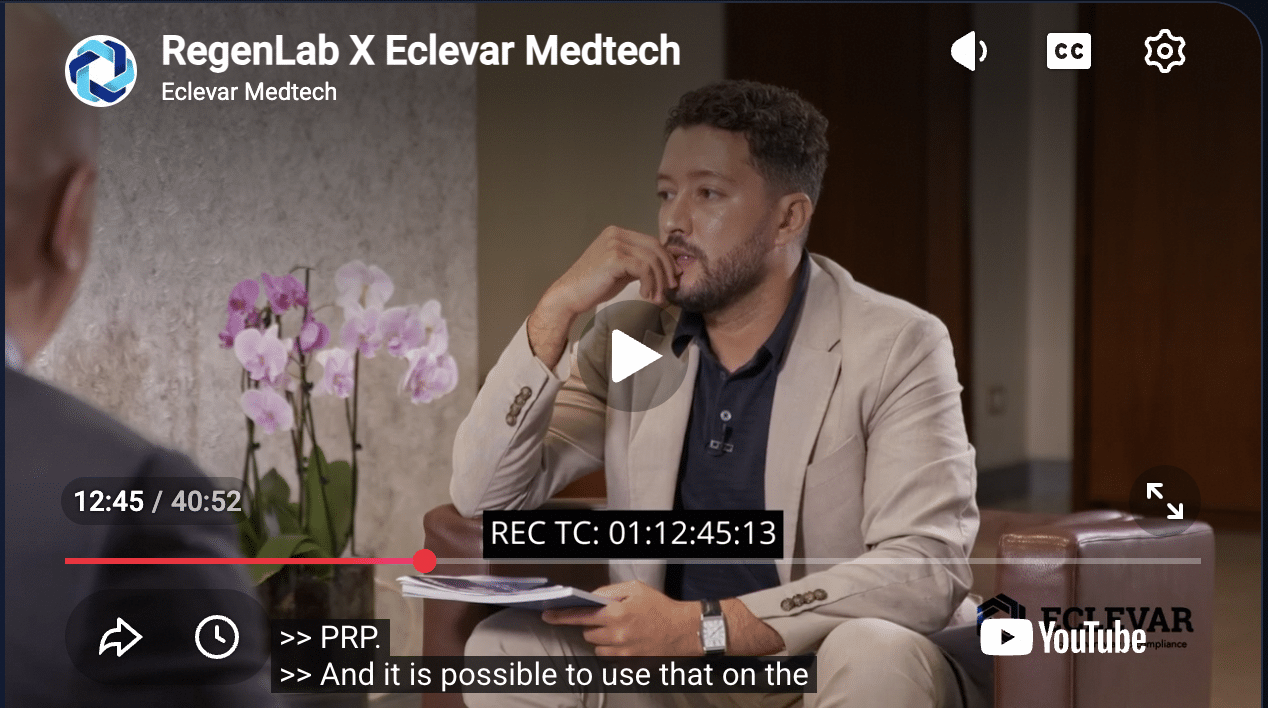
  • 160Subjects · 14 centers
  • 5EU countries

インタビューを見る

EclevarによるPMCFプログラムに関するRegenLabの動画推薦

近日公開。 Breakthrough Device Technology under the EU MDR, a whitepaper written with TÜV SÜD, co-authored by Dr Nikhil Khadabadi.

次の試験は勢いではなく、エビデンスで決める

早期フィージビリティの資料一式をお持ちください。それが何を明らかにし、何を明らかにしなかったのか、そしてどの道筋をエビデンスが支持するのかを、文書化された形でお持ち帰りいただけます。

規制上の参照先

  • FDA, Early Feasibility Studies (EFS) Program: fda.gov
  • FDA guidance, Investigational Device Exemptions (IDEs) for Early Feasibility Medical Device Clinical Studies, Including Certain First in Human (FIH) Studies: fda.gov
  • FDA guidance, Requests for Feedback and Meetings for Medical Device Submissions: The Q-Submission Program: fda.gov
  • Regulation (EU) 2017/745 on medical devices, in particular Article 62 and Annex XV: eur-lex.europa.eu
  • ISO 14155, clinical investigation of medical devices for human subjects, 2026 edition: iso.org

本ページは臨床開発の計画に関する一般的な情報であり、規制上または法律上の助言ではありません。

Reforming Clinical Evaluation of Medical Devices in Europe